



Cardiac Amyloidosis Treatment: ATTR, AL and Heart Failure Management
Cardiac amyloidosis is increasingly treatable, but treatment depends fundamentally on identifying the amyloid type. Transthyretin amyloid cardiomyopathy (ATTR-CM) and immunoglobulin light-chain (AL) cardiac amyloidosis arise from different precursor proteins and therefore require different disease-modifying therapies (1).
Management has two complementary goals: target the underlying amyloid-producing process and manage cardiac complications such as congestion, arrhythmias, conduction disease, and thromboembolic risk. Treatment should therefore be individualized according to amyloid type, disease stage, organ involvement and patient characteristics (1).
Key principle: ATTR and AL amyloidosis are not treated in the same way. Accurate amyloid typing should precede disease-specific therapy whenever possible.
Why Does the Amyloid Type Matter?
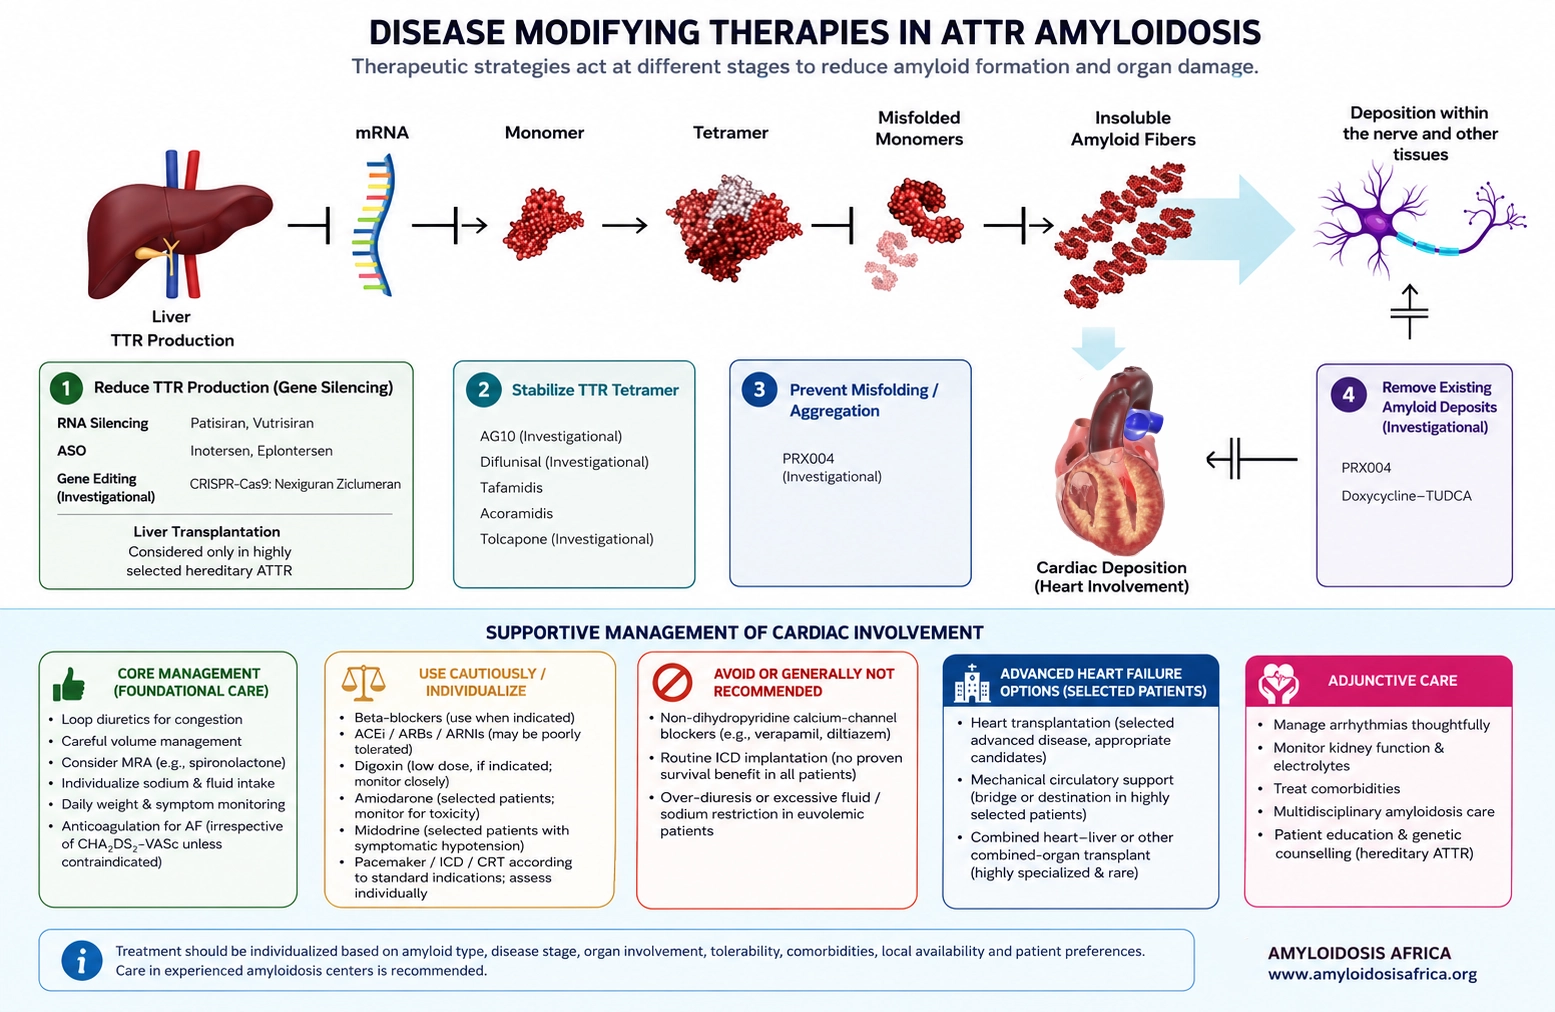
In ATTR amyloidosis, the precursor protein is transthyretin (TTR), which is produced predominantly by the liver. Current disease-modifying strategies aim either to stabilize circulating TTR so that it is less likely to dissociate and form amyloid, or to reduce hepatic production of TTR (2, 3, 4).
In AL amyloidosis, abnormal immunoglobulin light chains are produced by a clonal plasma-cell population. Treatment therefore targets the underlying plasma-cell clone to rapidly suppress production of amyloidogenic light chains (5).
Treatment of ATTR Cardiac Amyloidosis
Disease-modifying treatment for ATTR-CM has evolved rapidly. Two major therapeutic strategies are now clinically important: TTR stabilization and TTR gene silencing.
TTR Stabilizers
TTR normally circulates as a tetramer. Dissociation of this tetramer is an important step in the amyloid-forming process. TTR stabilizers bind to the tetramer and increase its stability, reducing dissociation into monomers that can misfold and aggregate.
Tafamidis
Tafamidis is a selective TTR stabilizer. In the landmark ATTR-ACT randomized trial involving patients with wild-type or hereditary transthyretin amyloid cardiomyopathy, tafamidis was associated with lower all-cause mortality and fewer cardiovascular-related hospitalizations compared with placebo. It also reduced the decline in functional capacity and quality of life (2).
Tafamidis acts by slowing further amyloid formation rather than directly removing established amyloid deposits. This reinforces the importance of recognizing and treating ATTR-CM before advanced irreversible cardiac dysfunction develops (1).
Acoramidis
Acoramidis is another TTR stabilizer developed to achieve near-complete stabilization of transthyretin. In the phase 3 ATTRibute-CM trial, acoramidis demonstrated significant clinical benefit in patients with ATTR-CM using a hierarchical composite outcome incorporating mortality, cardiovascular hospitalization, functional capacity and biochemical measures (3).
TTR Gene Silencing
Rather than stabilizing circulating transthyretin, gene-silencing therapies reduce the production of TTR by targeting the molecular pathway responsible for hepatic TTR synthesis.
Vutrisiran
Vutrisiran is a small interfering RNA therapeutic that reduces hepatic production of transthyretin. The HELIOS-B trial evaluated vutrisiran in patients with ATTR-CM. Treatment reduced the risk of death from any cause and recurrent cardiovascular events compared with placebo and preserved functional capacity and health status (4).
Two different strategies:
TTR stabilizers aim to keep the transthyretin tetramer stable.
TTR silencers reduce the amount of transthyretin produced by the liver.
TTR stabilizers aim to keep the transthyretin tetramer stable.
TTR silencers reduce the amount of transthyretin produced by the liver.
Treatment of AL Cardiac Amyloidosis
AL amyloidosis requires a fundamentally different approach. The objective is to rapidly suppress the plasma-cell clone responsible for producing toxic amyloidogenic light chains. Cardiac involvement is a major determinant of prognosis, making prompt diagnosis and treatment particularly important.
Daratumumab-Based Therapy
Daratumumab is a monoclonal antibody directed against CD38, which is expressed on plasma cells. The phase 3 ANDROMEDA trial evaluated subcutaneous daratumumab combined with bortezomib, cyclophosphamide and dexamethasone in newly diagnosed systemic AL amyloidosis.
The addition of daratumumab resulted in a substantially higher frequency of hematologic complete response and improved major organ deterioration–progression-free survival compared with bortezomib, cyclophosphamide and dexamethasone alone (5).
Autologous Stem Cell Transplantation
High-dose chemotherapy followed by autologous stem cell transplantation can be considered for carefully selected patients with AL amyloidosis. However, eligibility depends on factors including cardiac involvement, functional status, blood pressure, kidney function and overall treatment risk. Patients with advanced cardiac involvement may not be suitable candidates.
AL amyloidosis is a hematologic emergency when the heart is significantly involved. Rapid suppression of amyloidogenic light-chain production is an important therapeutic objective, and management should involve clinicians experienced in plasma-cell disorders and amyloidosis.
ATTR vs AL: Why the Treatments Cannot Be Interchanged
ATTR amyloidosis
Precursor protein: transthyretin
Main source: liver
Disease-modifying strategy: stabilize TTR or reduce TTR production
AL amyloidosis
Precursor protein: immunoglobulin light chain
Main source: clonal plasma cells
Disease-modifying strategy: rapidly suppress or eliminate the plasma-cell clone
Managing Heart Failure in Cardiac Amyloidosis
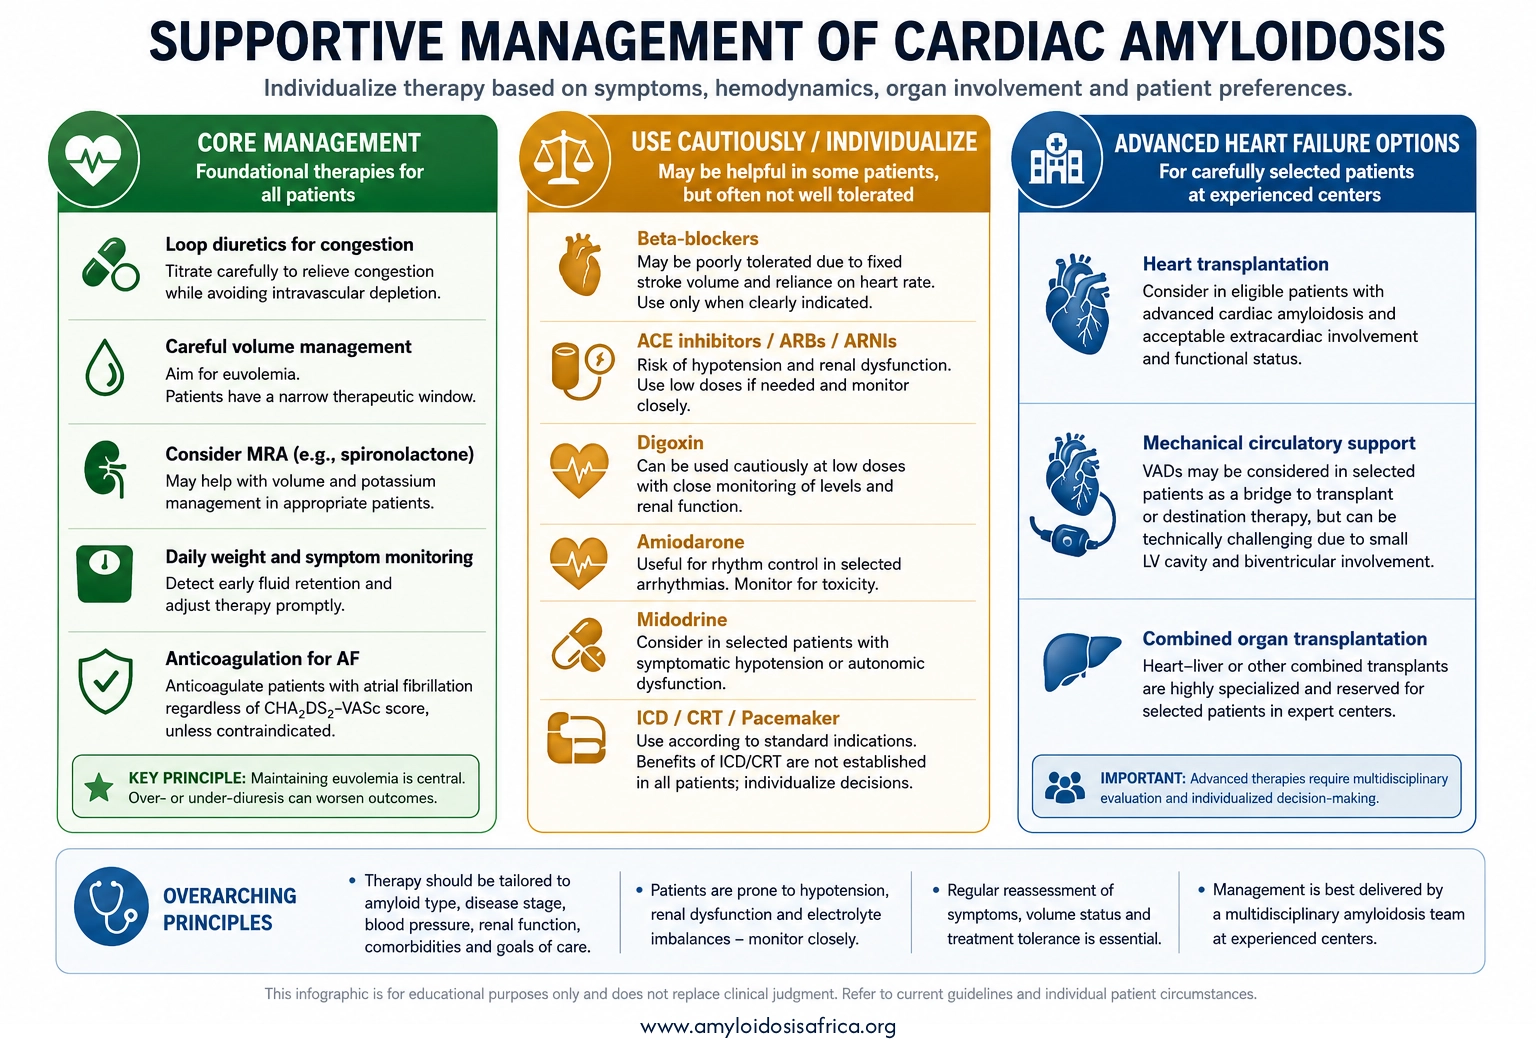
Heart failure management in cardiac amyloidosis differs in important ways from conventional heart failure management because the infiltrated ventricle is stiff, stroke volume may be relatively fixed and patients may be particularly sensitive to changes in preload, heart rate and blood pressure (1).
Diuretics and Volume Management
Loop diuretics are central to symptomatic management when congestion is present. Mineralocorticoid receptor antagonists may also be used in selected patients. However, careful titration is important because excessive diuresis can reduce ventricular filling and contribute to hypotension, kidney dysfunction and reduced cardiac output (1).
What About Standard Heart Failure Medications?
Conventional heart failure medications cannot simply be applied to every patient with cardiac amyloidosis in the same way they are used in other forms of heart failure.
Beta-blockers may be poorly tolerated in some patients because cardiac output can depend on maintaining an adequate heart rate. If required for another indication, they may need cautious dosing and close assessment of tolerance (1).
ACE inhibitors, angiotensin receptor blockers and angiotensin receptor-neprilysin inhibitors may also be poorly tolerated, particularly in patients with low blood pressure or autonomic dysfunction (1).
Clinical point: Heart failure treatment in cardiac amyloidosis should be individualized. Tolerance of conventional heart failure medications may differ substantially from that seen in other cardiomyopathies.
Atrial Fibrillation and Anticoagulation
Atrial fibrillation is common in cardiac amyloidosis and may be poorly tolerated because atrial contraction contributes importantly to ventricular filling in a stiff, restrictive heart.
Cardiac amyloidosis is also associated with an increased risk of intracardiac thrombus and thromboembolism. Current expert guidance recommends anticoagulation in patients with cardiac amyloidosis and atrial fibrillation regardless of the CHA2DS2-VASc score, unless contraindicated (1, 6).
Conduction Disease and Device Therapy
Amyloid infiltration can affect the cardiac conduction system, resulting in atrioventricular block, bundle branch disease and bradyarrhythmias. Permanent pacemaker implantation may therefore be required according to established pacing indications.
Decisions regarding implantable cardioverter-defibrillators and cardiac resynchronization therapy are more complex and should be individualized according to the patient’s arrhythmic risk, ventricular function, pacing requirements, disease stage and expected overall prognosis (1).
Why Multidisciplinary Care Matters
Amyloidosis is frequently a multisystem disease. Depending on the amyloid type and clinical phenotype, management may require collaboration between cardiology, hematology, neurology, nephrology, genetics, pathology, nuclear medicine and other specialties.
For hereditary ATTR amyloidosis, genetic counselling and appropriate evaluation of relatives may also form an important component of care.
Cardiac Amyloidosis Treatment in Africa
The expanding therapeutic landscape makes early and accurate diagnosis increasingly important. However, the availability and affordability of disease-modifying therapies, specialist multidisciplinary services, genetic testing and longitudinal monitoring may vary substantially between healthcare systems.
Important priorities for improving cardiac amyloidosis care across Africa include:
- Earlier recognition and accurate amyloid typing
- Development of multidisciplinary referral pathways
- Improved access to disease-modifying therapies
- Expanded access to genetic testing and counselling for ATTRv
- Education of healthcare professionals in amyloidosis management
- Development of regional referral networks and specialist expertise
- Generation of African data on treatment access, outcomes and disease phenotypes
Key Takeaways
- Cardiac amyloidosis treatment depends on the amyloid type.
- ATTR-CM can be treated using therapies that stabilize transthyretin or reduce its production.
- Tafamidis demonstrated reductions in mortality and cardiovascular-related hospitalizations in ATTR-ACT.
- Acoramidis is a TTR stabilizer with demonstrated clinical benefit in ATTR-CM.
- Vutrisiran reduces hepatic TTR production and demonstrated benefit in ATTR-CM in HELIOS-B.
- AL amyloidosis requires rapid treatment of the underlying plasma-cell disorder.
- Diuretics are central to the management of congestion, but volume status must be managed carefully.
- Conventional heart failure medications may be poorly tolerated in some patients and require individualized use.
- Patients with cardiac amyloidosis and atrial fibrillation generally require anticoagulation regardless of CHA2DS2-VASc score, unless contraindicated.
- Multidisciplinary care is important because amyloidosis frequently involves multiple organs.
References
- Kittleson MM, Ruberg FL, Ambardekar AV, Brannagan TH 3rd, Cheng RK, Clarke JO, et al. 2023 ACC Expert Consensus Decision Pathway on comprehensive multidisciplinary care for the patient with cardiac amyloidosis. J Am Coll Cardiol. 2023;81(11):1076-1126. doi:10.1016/j.jacc.2022.11.022.
- Maurer MS, Schwartz JH, Gundapaneni B, Elliott PM, Merlini G, Waddington-Cruz M, et al. Tafamidis treatment for patients with transthyretin amyloid cardiomyopathy. N Engl J Med. 2018;379(11):1007-1016. doi:10.1056/NEJMoa1805689.
- Gillmore JD, Judge DP, Cappelli F, Fontana M, Garcia-Pavia P, Gibbs S, et al. Efficacy and safety of acoramidis in transthyretin amyloid cardiomyopathy. N Engl J Med. 2024;390(2):132-142. doi:10.1056/NEJMoa2305434.
- Fontana M, Berk JL, Gillmore JD, Witteles RM, Grogan M, Drachman B, et al. Vutrisiran in patients with transthyretin amyloidosis with cardiomyopathy. N Engl J Med. 2025;392(1):33-44. doi:10.1056/NEJMoa2409134.
- Kastritis E, Palladini G, Minnema MC, Wechalekar AD, Jaccard A, Lee HC, et al. Daratumumab-based treatment for immunoglobulin light-chain amyloidosis. N Engl J Med. 2021;385(1):46-58. doi:10.1056/NEJMoa2028631.
- Heidenreich PA, Bozkurt B, Aguilar D, Allen LA, Byun JJ, Colvin MM, et al. 2022 AHA/ACC/HFSA guideline for the management of heart failure: executive summary. J Am Coll Cardiol. 2022;79(17):1757-1780. doi:10.1016/j.jacc.2021.12.011.
Medical Disclaimer
This article is intended for educational and informational purposes and is not a substitute for individualized medical advice, diagnosis or treatment. Treatment selection, drug availability, regulatory approval and eligibility criteria may vary between countries and patients. Clinical decisions should be made by appropriately qualified healthcare professionals based on the individual patient’s diagnosis, disease stage, comorbidities and locally applicable guidance.

[…] Treatment […]